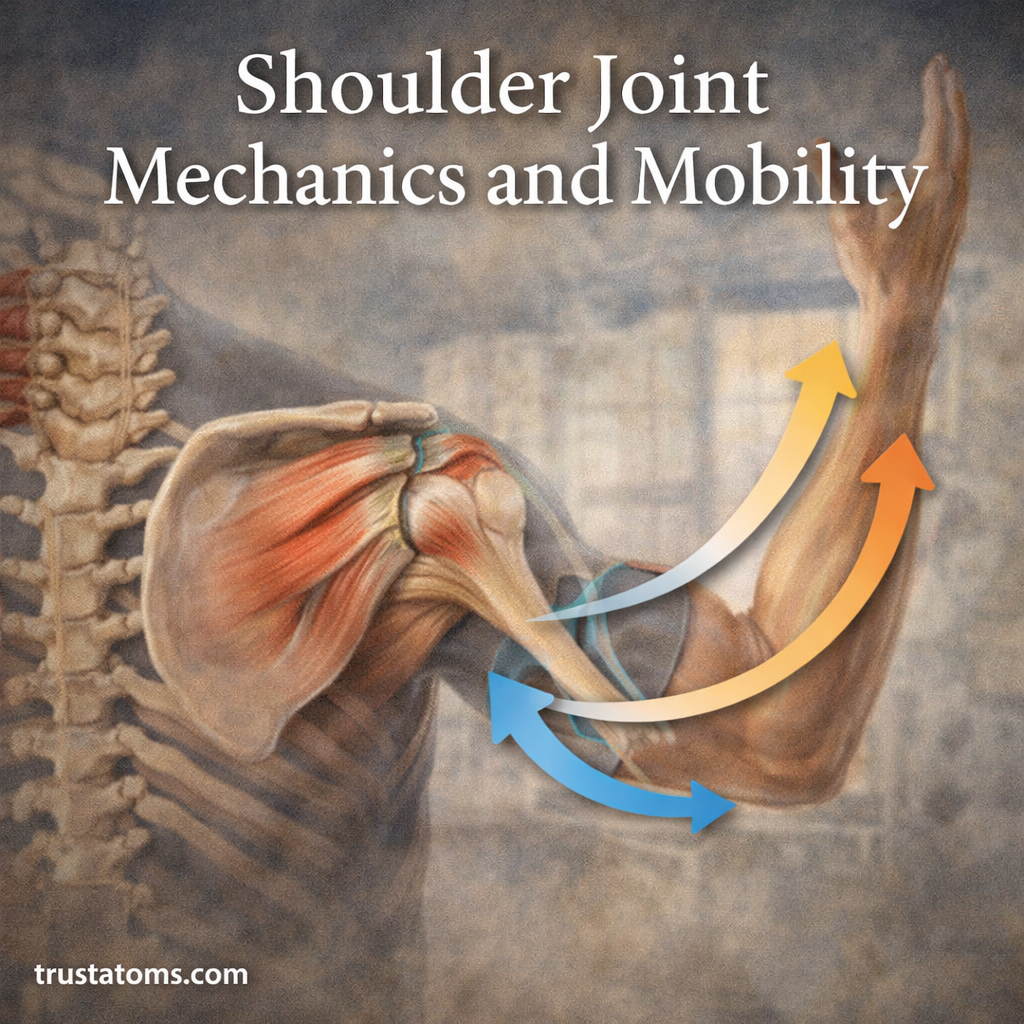
The shoulder joint is one of the most mobile and complex joints in the human body. It allows a wide range of motion necessary for daily activities such as reaching, lifting, throwing, and pushing.
Shoulder mechanics depend on coordinated movement between the upper arm, shoulder blade, and collarbone. Understanding these relationships is an important part of human anatomy because the shoulder must combine extensive mobility with enough stability to control the arm during movement.
Anatomy of the Shoulder Joint
The shoulder is a complex of several articulations rather than one isolated joint. Its main bones are the humerus, scapula, and clavicle, which connect the upper limb to the trunk.
- Glenohumeral joint: The ball-and-socket articulation between the humeral head and the glenoid cavity of the scapula.
- Acromioclavicular joint: Connects the clavicle to the acromion of the scapula and allows small adjustments during shoulder movement.
- Sternoclavicular joint: Connects the clavicle to the sternum and provides the main skeletal connection between the upper limb and axial skeleton.
- Scapulothoracic articulation: The functional movement of the scapula across the rib cage, rather than a conventional synovial joint.
These bones belong to the upper limb and shoulder girdle, described in The Appendicular Skeleton.
Supporting tissues include the joint capsule, ligaments, glenoid labrum, tendons, and surrounding muscles. Joint Stability and Supporting Structures explains how these components resist unwanted joint movement.
Shoulder Range of Motion and Movement Directions
The shoulder complex permits movement in several directions. This flexibility allows the hand to reach above the head, across the chest, behind the back, and away from the body.
| Movement | Description | Everyday Example |
|---|---|---|
| Flexion | Moving the arm forward and upward | Reaching toward a shelf |
| Extension | Moving the arm backward | Reaching behind the body |
| Abduction | Moving the arm away from the body’s midline | Raising the arm sideways |
| Adduction | Moving the arm toward the body | Lowering an outstretched arm |
| Internal rotation | Rotating the upper arm inward | Reaching toward the lower back |
| External rotation | Rotating the upper arm outward | Turning the forearm outward with the elbow bent |
| Circumduction | Combining movements into a circular pattern | Making controlled arm circles |
Normal movement varies with age, anatomy, flexibility, and measurement technique. Full overhead elevation typically involves motion at both the glenohumeral joint and the shoulder girdle, not the humerus alone.
Shoulder Joint Mechanics: Mobility and Stability
How the Ball-and-Socket Design Works
The rounded humeral head articulates with the relatively shallow glenoid cavity. This arrangement allows substantial rotation and movement but provides less bony restraint than a deeper socket.
The hip also has a ball-and-socket design, but its deeper socket favors greater structural stability. Hip Joint Mechanics and Stability explains how the two joints differ in their balance between movement and support.
Scapulohumeral Rhythm During Arm Elevation
Scapulohumeral rhythm describes the coordinated movement of the humerus and scapula during arm elevation. As the arm rises, the scapula rotates upward while the humerus moves relative to the glenoid.
A commonly taught approximation is a 2:1 ratio of glenohumeral elevation to scapular upward rotation. During approximately 180 degrees of arm elevation, this corresponds to about 120 degrees at the glenohumeral joint and 60 degrees of scapular rotation.
This ratio is not fixed throughout movement and varies between individuals. Coordinated scapular movement helps maintain the glenoid’s orientation and provides a suitable position for muscle action.
Muscles That Control Shoulder Movement

The Four Rotator Cuff Muscles
The rotator cuff consists of four muscles whose tendons surround the glenohumeral joint. Together, they help stabilize the humeral head while producing and controlling rotation.
- Supraspinatus: Assists arm abduction and contributes to joint stabilization.
- Infraspinatus: Produces external rotation and helps stabilize the humeral head.
- Teres minor: Assists external rotation and joint stability.
- Subscapularis: Produces internal rotation and supports anterior shoulder stability.
Larger Muscles and Scapular Control
The deltoid generates much of the force needed to lift the arm. Pectoralis major contributes to flexion, adduction, and internal rotation, while latissimus dorsi assists extension, adduction, and internal rotation.
Trapezius and serratus anterior coordinate scapular upward rotation during overhead movement. Their activity helps position the shoulder blade as the arm rises.
An Everyday Example: Placing a Box on a High Shelf
Imagine lifting a lightweight box from waist height onto a shelf above your head. The movement requires more than simply raising the upper arm.
- The deltoid and other shoulder muscles begin elevating the arm while the rotator cuff helps control the humeral head.
- The scapula rotates upward through coordinated action of the trapezius and serratus anterior.
- The clavicle moves at the sternoclavicular and acromioclavicular joints to accommodate scapular motion.
- The trunk, elbow, wrist, and hand contribute to positioning and supporting the box.
As the load increases, muscles must generate greater force and control. The movement illustrates why shoulder function depends on coordination across multiple joints rather than flexibility alone.
What Maintains Shoulder Stability?
The shoulder relies on both passive structures and active muscle control to maintain alignment during movement.
The glenoid labrum deepens the socket and contributes to stability. The joint capsule and ligaments restrict excessive translation, while rotator cuff muscles help keep the humeral head centered against the glenoid.
Stability is not the same as stiffness. A healthy shoulder needs sufficient freedom to move while resisting unwanted displacement, especially when lifting, throwing, or supporting weight.
Factors That Limit Shoulder Mobility
Several factors can restrict shoulder movement or change how the arm and scapula coordinate.
- Muscle and tendon stiffness: Reduced tissue extensibility may limit particular movements.
- Joint capsule restrictions: Conditions such as adhesive capsulitis can substantially reduce active and passive movement.
- Scapular movement changes: Altered muscle coordination may affect overhead arm mechanics.
- Pain or injury: Discomfort, weakness, or tissue damage can limit movement even without a fixed structural restriction.
- Thoracic mobility: Movement of the upper back can influence shoulder positioning during reaching.
Posture may affect available movement in certain positions, but no single resting posture guarantees healthy shoulders or prevents injury.
Common Shoulder Problems and Their Mechanics
Shoulder symptoms can arise from several different conditions, and similar symptoms do not always indicate the same injury.
- Rotator cuff tendinopathy or tears: May cause pain, weakness, and difficulty lifting the arm.
- Shoulder instability: Excessive humeral head movement may lead to subluxation or dislocation.
- Subacromial pain: Can involve irritated tendons or nearby tissues during arm elevation.
- Adhesive capsulitis: Produces progressive stiffness and restriction of shoulder motion.
These conditions may involve injury, age-related tissue changes, inflammation, or other factors. They should not automatically be attributed to poor posture or incorrect movement technique.
Maintaining Shoulder Mobility and Strength
Shoulder function benefits from appropriate strength, flexibility, and movement control. General approaches include gradually strengthening the rotator cuff and scapular muscles, maintaining comfortable movement in different directions, and adjusting activity loads to individual capacity.
Progressive resistance exercises can improve the ability to control loads, while mobility exercises may help maintain usable movement. Exercise selection and intensity should account for existing injuries, pain, and individual limitations.
Persistent pain, substantial weakness, or sudden loss of movement warrants professional evaluation. A suspected dislocation or serious injury requires prompt medical attention.
Frequently Asked Questions
Why does the shoulder have such a large range of motion?
The glenohumeral joint has a rounded humeral head and relatively shallow socket, allowing movement in several directions. Additional motion at the scapula and clavicle increases the overall reach of the shoulder complex.
What is scapulohumeral rhythm?
Scapulohumeral rhythm is the coordination between humeral movement and scapular rotation during arm elevation. A 2:1 ratio is a common teaching approximation, but the actual relationship varies throughout movement.
Which muscles stabilize the shoulder joint?
The supraspinatus, infraspinatus, teres minor, and subscapularis form the rotator cuff and help control the humeral head. Larger muscles, including the deltoid, trapezius, and serratus anterior, also contribute to coordinated shoulder movement and stability.
Shoulder mobility results from coordinated movement at the glenohumeral, acromioclavicular, sternoclavicular, and scapulothoracic articulations. The rotator cuff and surrounding muscles help balance this freedom of movement with stability, allowing the arm to reach, lift, and support loads across a wide range of positions.
This article is for general education and is not medical advice. Talk to a qualified health professional about any medical concern.
Sources: Gray’s Anatomy for Students by Drake, Vogl, and Mitchell; Kinesiology of the Musculoskeletal System by Donald A. Neumann; Clinical Sports Medicine by Brukner and Khan.