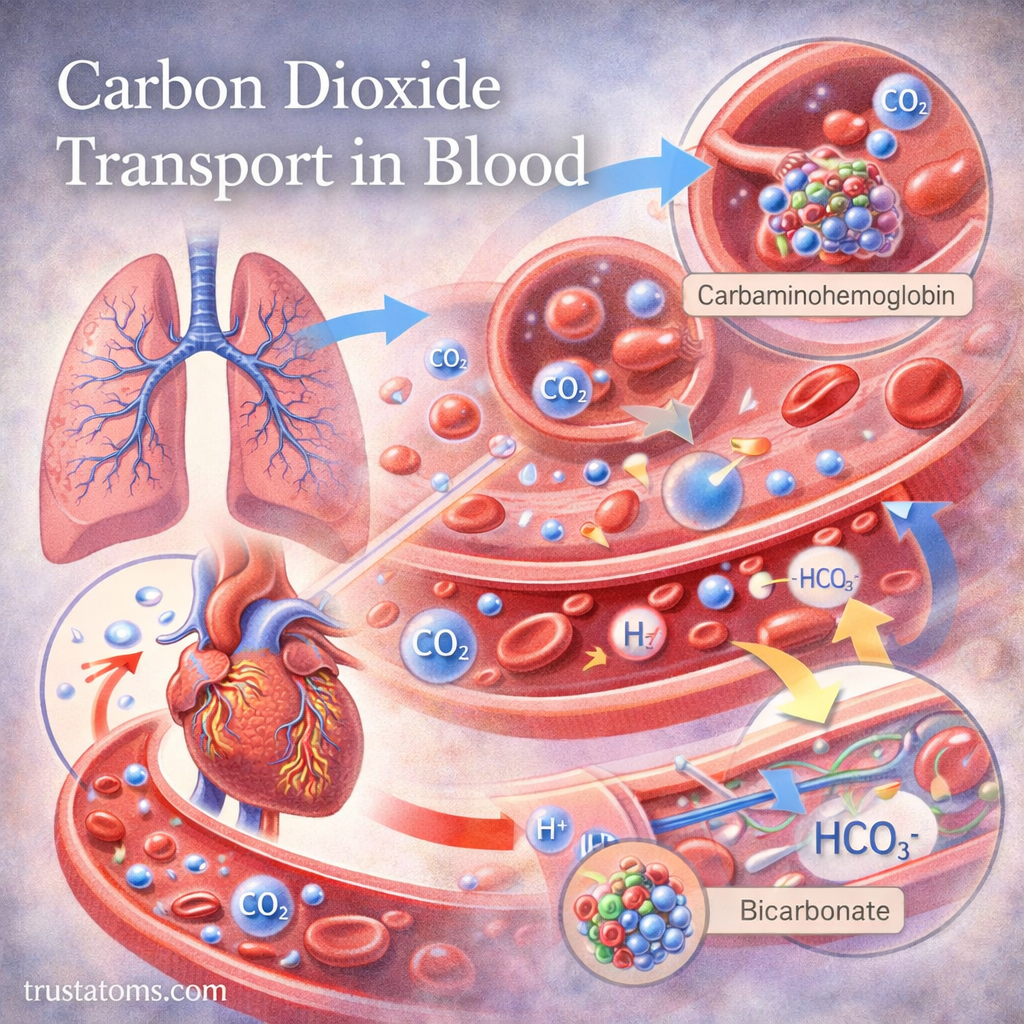
Carbon dioxide (CO₂) travels through the bloodstream in three main forms: bicarbonate ions, CO₂ bound to proteins, and dissolved CO₂. Most is converted into bicarbonate inside red blood cells, allowing blood to carry carbon dioxide from active tissues to the lungs for exhalation.
This transport process also helps regulate blood acidity because carbon dioxide participates in chemical reactions involving hydrogen ions. Understanding these reactions connects respiratory physiology with human anatomy, showing how blood, lungs, and tissues cooperate to maintain stable internal conditions.
What Is Carbon Dioxide and Where Does It Come From?
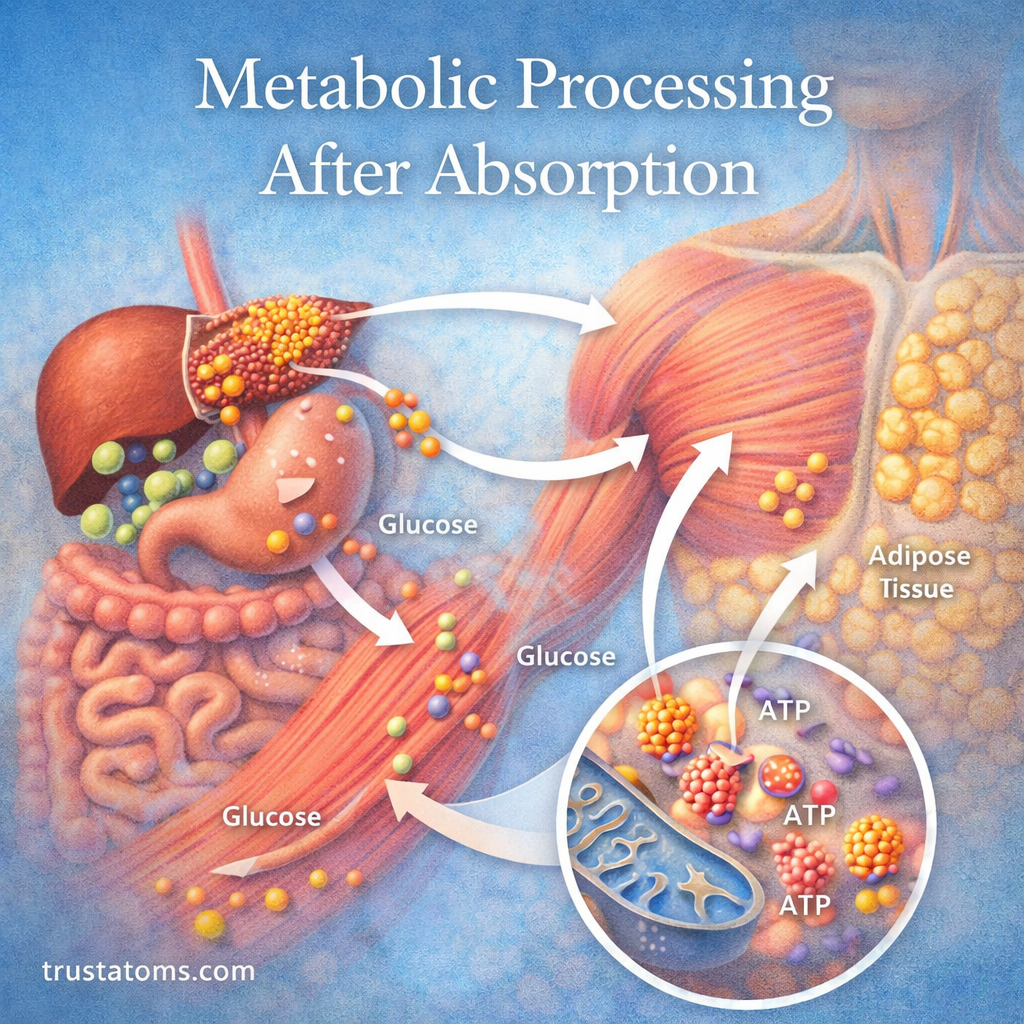
Carbon dioxide is produced during cellular metabolism as the body extracts energy from nutrients. Important CO₂-producing reactions occur in mitochondria, including pyruvate oxidation and the citric acid cycle.
Because cells continually generate CO₂, the circulatory system must transport it to the lungs. If carbon dioxide accumulates faster than it can be eliminated, arterial CO₂ levels can rise and disturb acid-base balance.
Transporting CO₂ is only part of the process. Carbon dioxide removal and ventilation explains how breathing replaces alveolar air and allows carbon dioxide to leave the body.
The Three Forms of Carbon Dioxide Transport
Carbon dioxide is carried in several forms because no single transport method accounts for all of the CO₂ moving through blood. The proportions are approximate and vary with physiological conditions.
| Transport form | Approximate share | How CO₂ is carried |
|---|---|---|
| Bicarbonate ions | About 70% | Converted into bicarbonate, which travels mainly in plasma |
| Bound to proteins | About 20–25% | Attached to proteins, particularly hemoglobin |
| Dissolved CO₂ | About 5–10% | Dissolved directly in blood |
Dissolved Carbon Dioxide
A relatively small portion of carbon dioxide remains dissolved in plasma and the fluid inside blood cells. Although this is not the largest transport fraction, dissolved CO₂ determines the partial pressure of carbon dioxide, or PCO₂.
Differences in PCO₂ drive diffusion between tissues and blood and between pulmonary blood and alveolar air. Dissolved CO₂ also participates in the chemical reactions that influence blood pH.
Carbon Dioxide Bound to Hemoglobin
Carbon dioxide can bind to hemoglobin in red blood cells. This produces carbaminohemoglobin, one form of CO₂ bound to proteins.
CO₂ binds mainly to amino groups on the globin portion of hemoglobin, not to the iron-containing heme sites that bind oxygen. This distinction allows hemoglobin to participate in transporting both gases through different binding mechanisms.
Carbon Dioxide Converted Into Bicarbonate
Most transported carbon dioxide is converted into bicarbonate ions (HCO₃⁻). The conversion occurs rapidly inside red blood cells because they contain carbonic anhydrase, an enzyme that accelerates the reaction between CO₂ and water.
The reaction can be represented as:
CO₂ + H₂O ⇌ H₂CO₃ ⇌ H⁺ + HCO₃⁻
Carbonic acid (H₂CO₃) forms briefly before dissociating into hydrogen ions and bicarbonate. Many bicarbonate ions then leave red blood cells and enter plasma, where they can be transported toward the lungs.
How the Chloride Shift Supports Bicarbonate Transport
As bicarbonate leaves a red blood cell, chloride ions move inward through an anion exchange protein. This process, called the chloride shift, helps maintain electrical balance across the cell membrane.
In the lungs, the process reverses. Bicarbonate returns to red blood cells while chloride moves outward, allowing bicarbonate to be converted back into CO₂ for elimination.
Without these coordinated exchanges, transporting large amounts of carbon dioxide as bicarbonate would be less efficient.
The Role of Hemoglobin in Carbon Dioxide Transport
Hemoglobin does more than carry oxygen and bind some carbon dioxide. It also buffers hydrogen ions produced during bicarbonate formation, helping limit changes in blood pH.
Hemoglobin’s ability to carry CO₂ and buffer hydrogen ions changes depending on whether it is oxygenated. Deoxygenated hemoglobin generally accepts hydrogen ions and carbon dioxide more readily than oxygenated hemoglobin.
This relationship is called the Haldane effect. In tissues, oxygen release helps blood take up CO₂. In the lungs, oxygen binding promotes CO₂ release.
Oxygen saturation and hemoglobin binding explains how oxygen availability changes hemoglobin’s oxygen-binding state and influences gas transport.
What Happens to Carbon Dioxide in Tissues and Lungs?
Carbon dioxide transport depends on pressure differences and reversible chemical reactions at opposite ends of the circulation.
In Body Tissues
- Cells produce CO₂ during metabolism, raising local CO₂ partial pressure.
- CO₂ diffuses into nearby capillary blood and red blood cells.
- Carbonic anhydrase accelerates bicarbonate formation.
- Bicarbonate enters plasma through the chloride shift, while some CO₂ remains dissolved or binds to proteins.
In the Lungs
- Blood reaches pulmonary capillaries surrounding the alveoli.
- Bicarbonate reenters red blood cells and is converted back into CO₂.
- Oxygen binding to hemoglobin encourages CO₂ release.
- CO₂ diffuses into the alveoli and is removed during exhalation.
The same reversible reactions that help load CO₂ in tissues allow blood to unload it efficiently in the lungs.
How Carbon Dioxide Transport Affects Blood pH
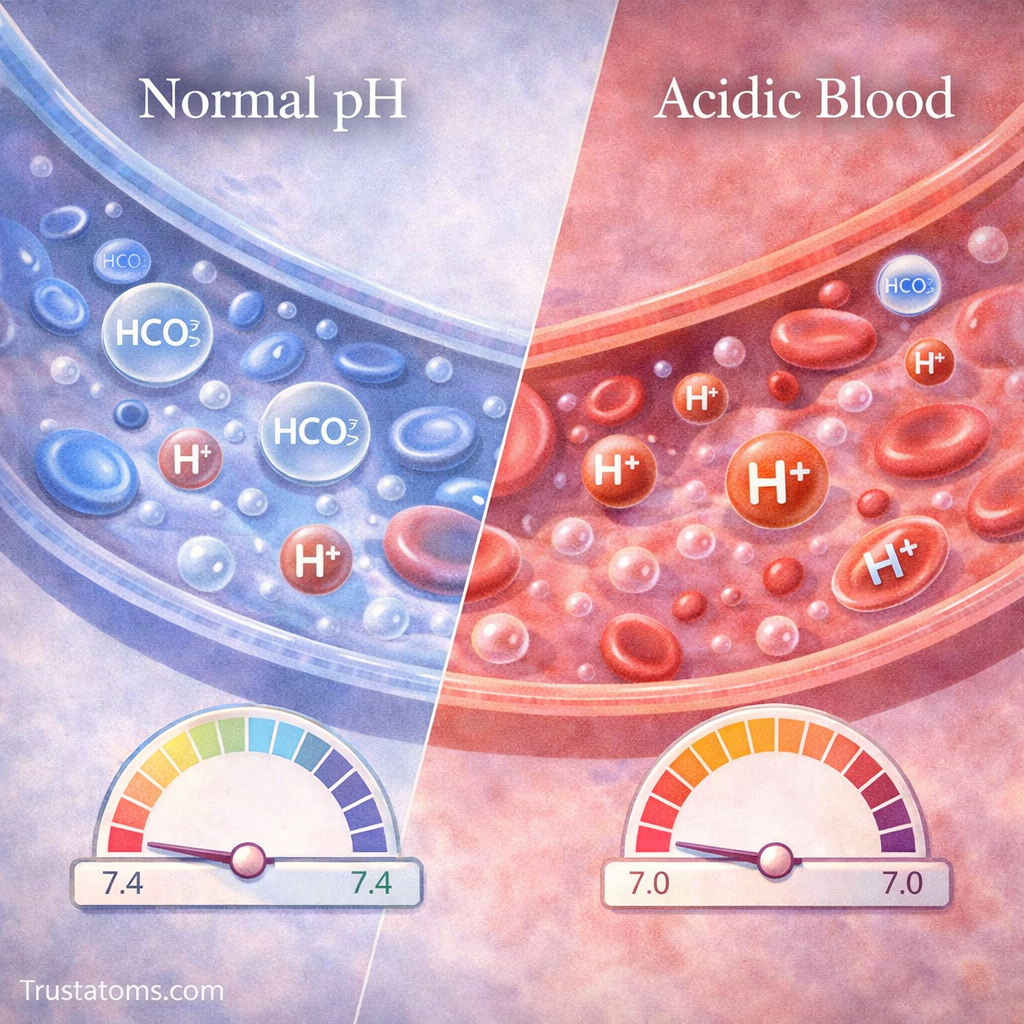
Carbon dioxide influences blood pH through the bicarbonate buffer system. When CO₂ rises while other conditions remain similar, the reaction shifts toward producing more hydrogen ions, which lowers pH.
When CO₂ falls, hydrogen ion concentration tends to decrease and pH rises. Normal arterial blood pH is approximately 7.35–7.45, making careful regulation necessary for normal cellular function.
Blood buffers help resist rapid pH changes, while the lungs regulate CO₂ elimination and the kidneys adjust bicarbonate and acid handling over longer periods.
How Carbon Dioxide Transport Changes During Exercise
During physical activity, working muscles increase their metabolic rate and generally produce more carbon dioxide. Blood flow and ventilation rise to help transport and eliminate the additional CO₂.
For example, when someone begins running, the leg muscles generate more CO₂ than they do at rest. The increased CO₂ moves into capillary blood, much of it becomes bicarbonate, and the circulation carries it to the lungs.
Breathing becomes deeper and often faster, increasing alveolar ventilation. During moderate exercise, these adjustments usually allow arterial CO₂ to remain close to its resting level despite greater production.
How the Body Maintains CO₂ Balance
Maintaining carbon dioxide balance requires matching CO₂ elimination to metabolic production. Brainstem respiratory centers adjust ventilation using information from chemoreceptors that respond to changes in CO₂, acidity, and oxygen.
When arterial CO₂ rises, ventilation usually increases. If ventilation becomes inadequate, CO₂ may accumulate, producing hypercapnia and potentially respiratory acidosis.
Excessive alveolar ventilation can lower CO₂ below normal, producing hypocapnia and potentially respiratory alkalosis. Acid–base balance and CO₂ regulation examines how respiratory and kidney responses help stabilize blood chemistry.
Factors That Can Disrupt Carbon Dioxide Transport
Effective CO₂ transport depends on functioning blood cells, adequate circulation, and sufficient pulmonary ventilation.
- Reduced blood flow: Can limit the movement of CO₂ away from tissues.
- Abnormal ventilation: May cause CO₂ retention or excessive CO₂ loss.
- Lung disease: Can impair ventilation and the matching of airflow with pulmonary blood flow.
- Changes in hemoglobin: Can affect the blood’s buffering capacity and some aspects of CO₂ carriage.
These disturbances do not all produce the same symptoms or changes in blood chemistry. Their effects depend on the underlying cause and the body’s ability to compensate.
Frequently Asked Questions
What is the main form of carbon dioxide transport in blood?
Most carbon dioxide is transported as bicarbonate ions. CO₂ is converted into bicarbonate primarily inside red blood cells, and much of the bicarbonate then travels through plasma toward the lungs.
Does carbon dioxide bind to the same part of hemoglobin as oxygen?
No. Oxygen binds to iron-containing heme groups, while carbon dioxide binds mainly to amino groups on the globin portion of hemoglobin. These different binding sites allow hemoglobin to participate in transporting both gases.
Why does increased carbon dioxide lower blood pH?
Carbon dioxide reacts with water to form carbonic acid, which can release hydrogen ions. When CO₂ increases without a matching compensatory change in bicarbonate, hydrogen ion concentration tends to rise and blood pH decreases.
Carbon dioxide transport relies on bicarbonate formation, protein binding, and dissolved CO₂ working together as blood travels between tissues and lungs. Red blood cells accelerate these reactions, while hemoglobin helps buffer hydrogen ions and facilitates gas exchange. The reversible nature of these processes allows the body to remove metabolic CO₂ while regulating blood acidity.
This article is for general education and is not medical advice. Talk to a qualified health professional about any medical concern.
Sources: Guyton and Hall Textbook of Medical Physiology; West’s Respiratory Physiology: The Essentials; OpenStax Anatomy and Physiology 2e.