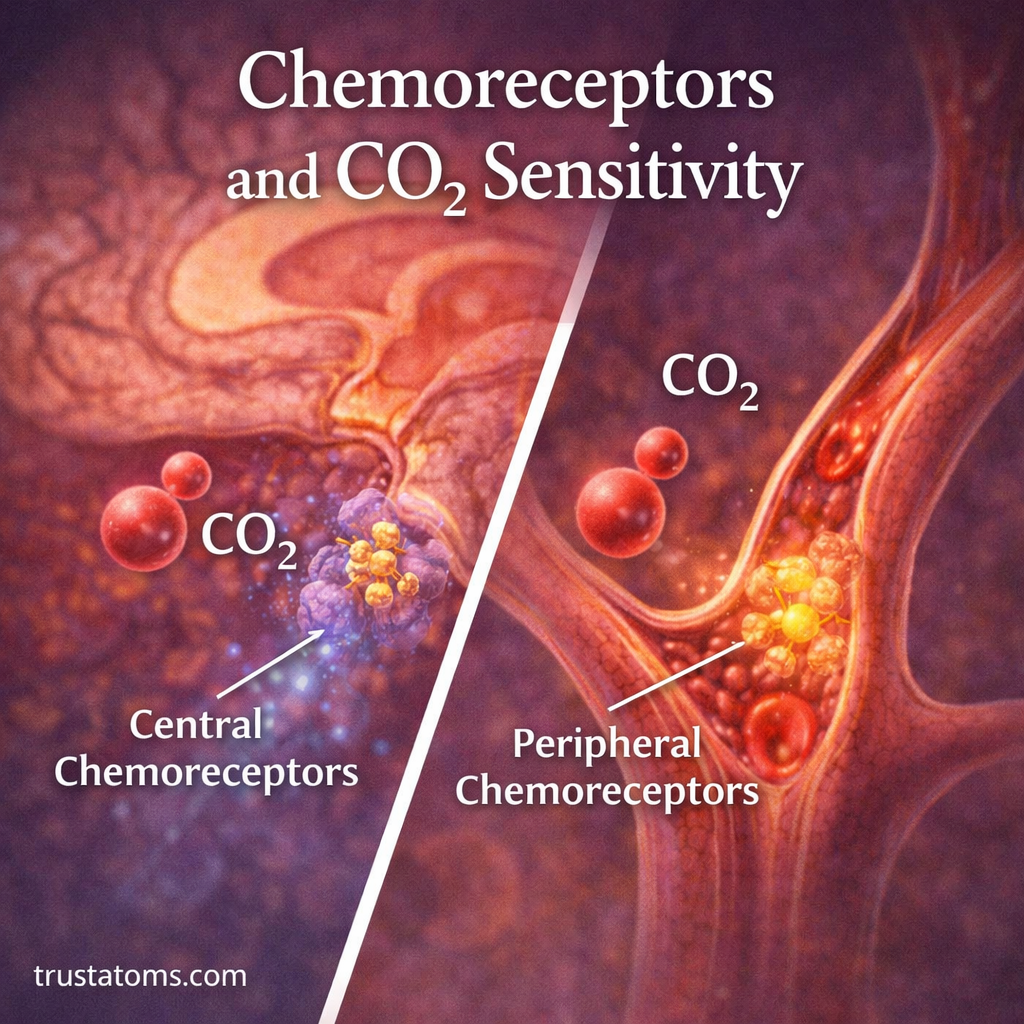
Chemoreceptors are specialized sensory cells and neural structures that detect chemical changes related to carbon dioxide (CO₂), oxygen, and acidity, helping the body regulate breathing automatically. CO₂ sensitivity describes how strongly the respiratory control system responds to changes in carbon dioxide, usually by adjusting the depth and frequency of breaths.
This feedback system connects the lungs, blood vessels, and brainstem, making it an important example of how structures studied in human anatomy work together. It helps keep blood gases and acid-base conditions within ranges compatible with normal cellular function, even as activity levels change.
What Are Chemoreceptors?
Chemoreceptors involved in breathing control detect changes in the chemical environment of the blood or fluid surrounding the brain. Their responses influence respiratory centers in the brainstem, which adjust ventilation to help maintain stable carbon dioxide, oxygen, and pH levels.
Carbon dioxide is particularly important because it participates in chemical reactions that affect hydrogen ion concentration and acidity. The connection between ventilation, bicarbonate, and blood pH is explored in acid-base balance and CO₂ regulation.
Chemoreceptor responses also help match the removal of metabolically produced carbon dioxide to the body’s needs. The relationship between breathing and gas elimination is explained in carbon dioxide removal and ventilation.
Central and Peripheral Chemoreceptors
Two major groups of chemoreceptors contribute to respiratory regulation. They monitor related chemical changes but differ in location, sensitivity, and how they communicate with the brainstem.
Central Chemoreceptors in the Brainstem
Central chemoreceptors are associated with regions of the medulla oblongata. They respond primarily to changes in hydrogen ion concentration in the brain’s extracellular fluid, which is influenced by carbon dioxide entering from the blood.
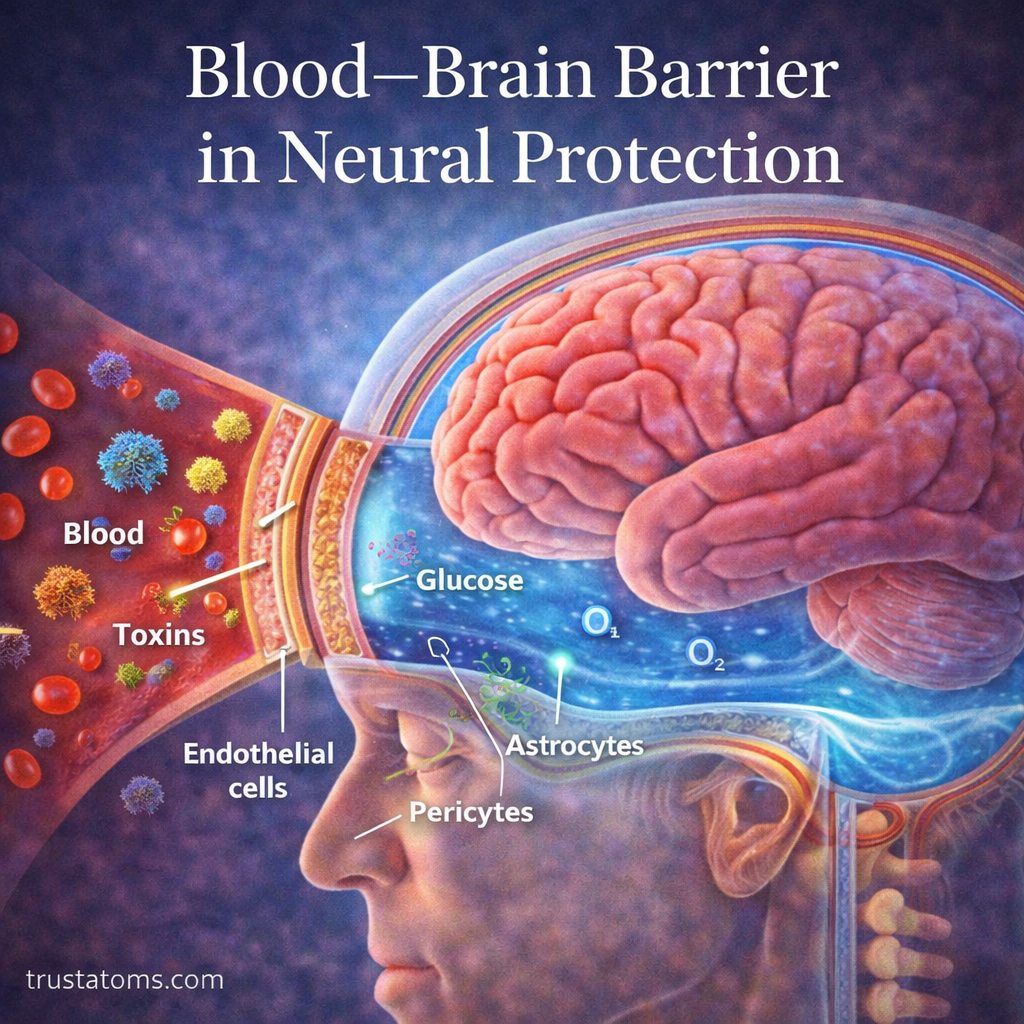
CO₂ crosses the blood-brain barrier relatively easily. Once in the brain’s surrounding fluid, it reacts with water and produces hydrogen ions. The resulting decrease in pH stimulates central chemosensitive mechanisms that increase ventilation.
Central chemoreceptors do not directly measure arterial oxygen concentration and are not the main sensors for low blood oxygen.
Peripheral Chemoreceptors in the Arteries
Peripheral chemoreceptors are located in the carotid bodies near the branching of the common carotid arteries and in the aortic bodies near the aortic arch.
They respond to changes in arterial oxygen pressure, carbon dioxide pressure, and pH. Carotid bodies are especially important for detecting substantial decreases in arterial oxygen.
Signals from the carotid bodies travel mainly through the glossopharyngeal nerve, while those from the aortic bodies travel through the vagus nerve. Both communicate with respiratory control networks in the brainstem.
How Central and Peripheral Chemoreceptors Compare
| Feature | Central Chemoreceptors | Peripheral Chemoreceptors |
|---|---|---|
| Location | Brainstem, particularly medullary regions | Carotid and aortic bodies |
| Main stimulus | Changes in brain extracellular fluid pH related to CO₂ | Arterial oxygen, CO₂, and pH changes |
| Low oxygen detection | Not a direct primary function | Major function, especially in carotid bodies |
| Response | Contributes strongly to sustained CO₂-related ventilation | Provides rapid responses to changes in blood chemistry |
Why CO₂ Is a Major Driver of Breathing
Under ordinary conditions in healthy adults, changes in arterial CO₂ pressure provide a major chemical stimulus for adjusting ventilation. Even modest increases in CO₂ can increase respiratory drive because they alter acidity in the blood and brain’s extracellular fluid.
Respiratory networks within the medulla and pons coordinate this response. Their organization is described in breathing control centers in the brainstem, while neural control of breathing explains how neural signals coordinate respiratory muscles.
Although CO₂ is a major regulator, breathing is also influenced by oxygen availability, voluntary control, exercise-related signals, and sensory feedback from the lungs and respiratory muscles.
The Connection Between CO₂, pH, and Ventilation
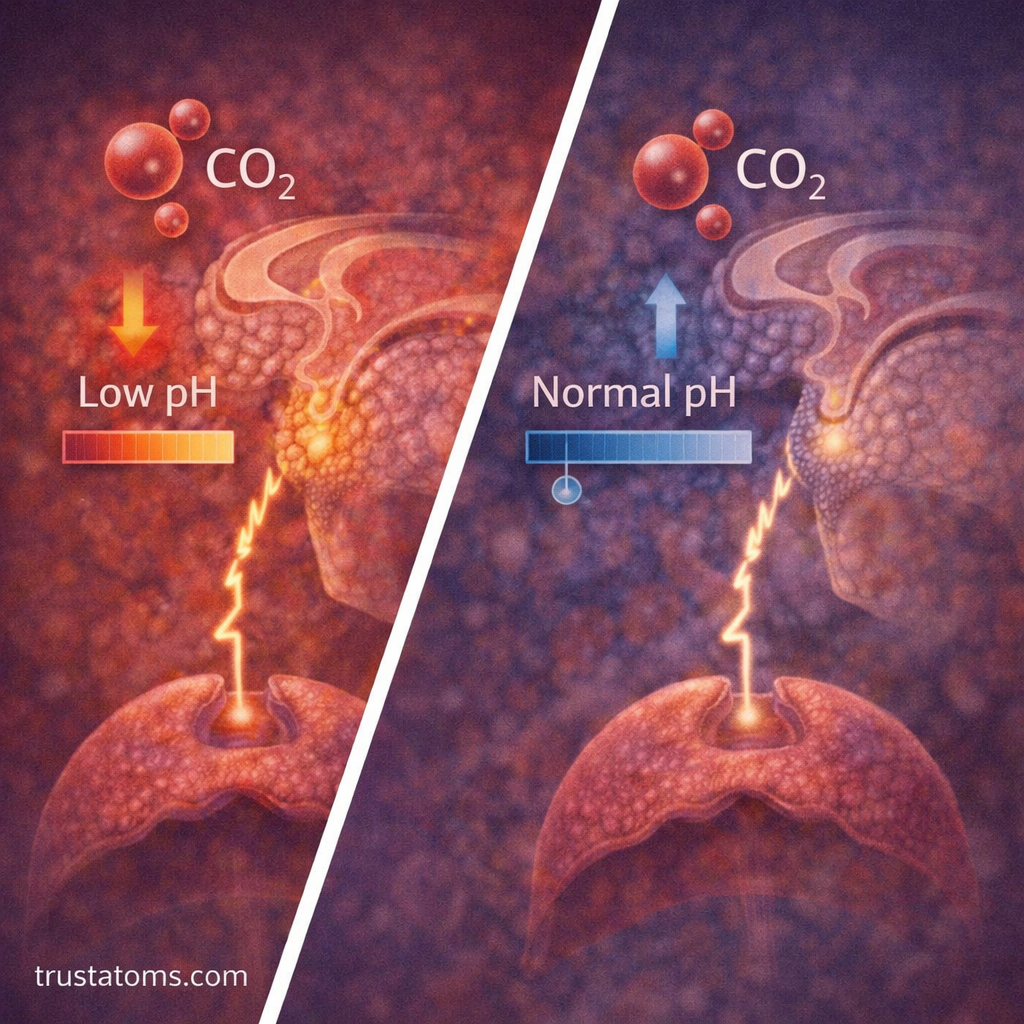
Carbon dioxide reacts reversibly with water to form carbonic acid, which can dissociate into hydrogen ions and bicarbonate. As CO₂ increases, hydrogen ion concentration tends to rise, lowering pH unless other processes compensate.
The respiratory feedback response follows a sequence:
- Metabolism produces CO₂, which enters the bloodstream.
- If CO₂ production exceeds removal, arterial CO₂ pressure rises.
- CO₂-related acidity changes stimulate central and peripheral chemoreceptors.
- Brainstem respiratory networks increase the depth and often the frequency of breathing.
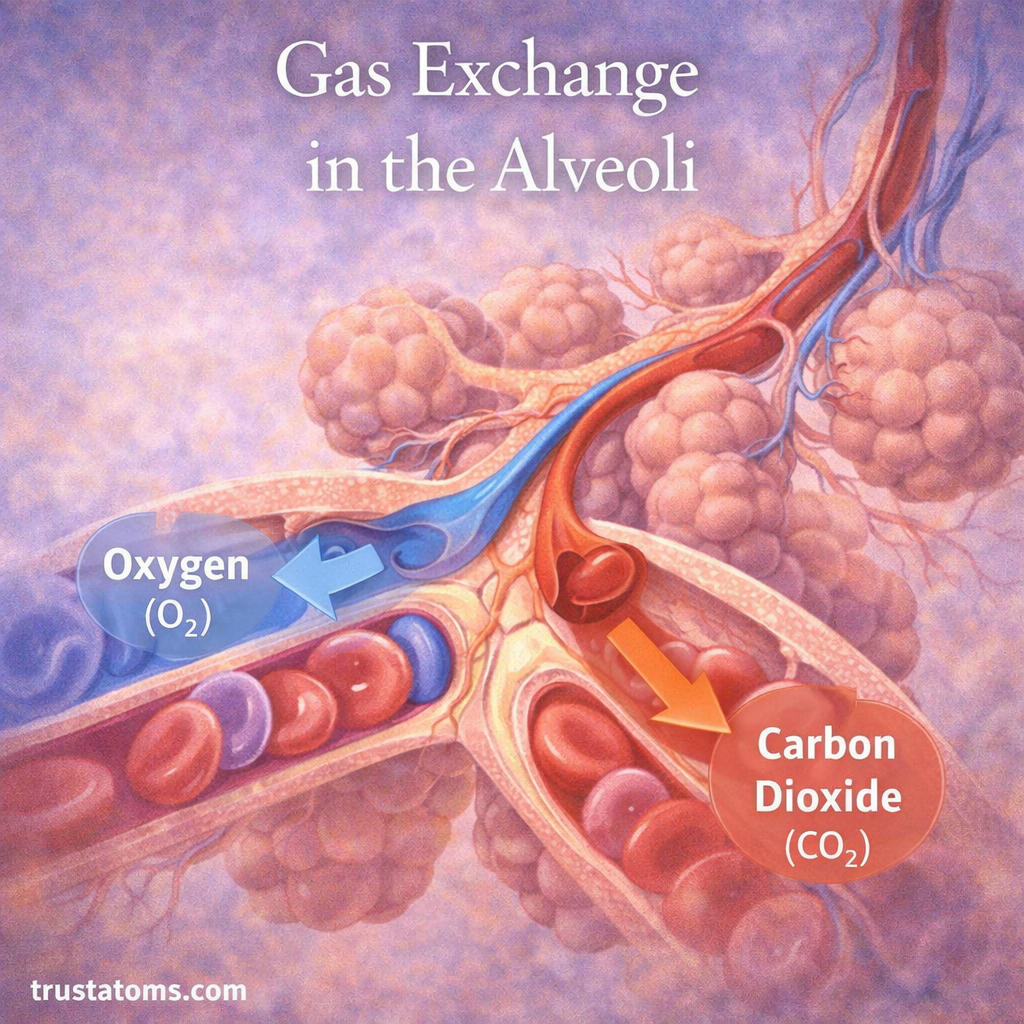
- Greater alveolar ventilation removes more CO₂, helping restore chemical balance.
This is an example of negative feedback: a change in CO₂ triggers a response that opposes the original disturbance.
What Happens When CO₂ Levels Rise or Fall?
Normal arterial CO₂ pressure is approximately 35–45 mmHg in healthy adults at sea level. This measurement, called PaCO₂, reflects the balance between CO₂ production and alveolar ventilation.
When PaCO₂ rises, respiratory drive generally increases. Elevated CO₂ may occur when ventilation is insufficient to remove the amount produced by metabolism.
When PaCO₂ falls, chemoreceptor stimulation generally decreases. Excessive ventilation can lower CO₂ enough to contribute to lightheadedness or tingling, partly because reduced CO₂ changes blood pH and cerebral blood flow.
CO₂ Sensitivity During Exercise and Breath-Holding
Exercise increases metabolic activity and CO₂ production. Ventilation rises through a combination of neural signals associated with movement and chemical feedback, helping maintain arterial CO₂ near its usual range during many levels of steady exercise.
Breath-holding provides a more direct example of CO₂ sensitivity. When someone voluntarily stops breathing, the body continues producing CO₂. As CO₂ accumulates, increasing chemical stimulation contributes to the growing urge to breathe.
The urge to breathe is not a reliable indicator of adequate oxygen. Deliberate hyperventilation before breath-holding can dangerously delay the urge while oxygen falls, creating a risk of loss of consciousness, particularly underwater.
How Low Oxygen Affects Chemoreceptors
Peripheral chemoreceptors become increasingly active as arterial oxygen pressure falls, especially when it drops below approximately 60 mmHg. This response helps increase ventilation when oxygen availability is substantially reduced.
At high altitude, lower atmospheric pressure reduces the oxygen pressure available for gas exchange. Carotid body stimulation promotes increased breathing, although the resulting reduction in CO₂ and rise in pH can initially oppose part of the ventilatory response.
With continued altitude exposure, physiological adjustments help support increased ventilation. The response varies among individuals and depends on altitude and duration of exposure.
When Respiratory Chemical Control Is Disrupted
Respiratory control can be altered by neurological injury, certain medications, and chronic respiratory disorders. Opioids, for example, can suppress brainstem respiratory drive and reduce responsiveness to rising CO₂, potentially causing dangerous hypoventilation.
Some people with chronic hypercapnia develop altered responses to CO₂ over time. However, it is inaccurate to assume that all people with chronic lung disease breathe only because their oxygen level is low. Respiratory regulation remains influenced by multiple interacting mechanisms.
Supporting Healthy Respiratory Control
Normal respiratory regulation depends on healthy lungs, functioning neural pathways, and effective respiratory muscles. Regular physical activity, avoiding tobacco smoke, and appropriate management of respiratory conditions can support overall respiratory health.
Breathing depth and frequency are adjusted continuously rather than remaining fixed. The relationship between these adjustments and effective air movement is explained in respiratory rate and ventilation control.
Persistent breathlessness, unusual breathing patterns, or unexplained episodes of reduced breathing should be evaluated by a qualified health professional rather than managed through unverified breathing exercises.
Frequently Asked Questions
Do chemoreceptors directly measure carbon dioxide?
Central chemoreceptors mainly respond to acidity changes produced when CO₂ enters brain extracellular fluid. Peripheral chemoreceptors respond to changes in arterial CO₂, pH, and oxygen through specialized cellular sensing mechanisms.
Why does holding your breath become uncomfortable?
CO₂ accumulates while breathing is stopped, increasing chemical stimulation of respiratory control networks. This contributes to the urge to breathe, along with other neural and mechanical signals.
Does oxygen or carbon dioxide control breathing more strongly?
In healthy adults under ordinary conditions, CO₂-related chemical feedback is a major regulator of ventilation. Low oxygen becomes an increasingly strong stimulus when arterial oxygen pressure falls substantially, and both signals can interact.
Chemoreceptors connect changes in blood chemistry with automatic adjustments in ventilation. Central chemosensitive mechanisms respond strongly to CO₂-related acidity, while peripheral receptors provide additional information about oxygen, CO₂, and arterial pH. Together with brainstem respiratory networks, these sensors help maintain stable gas exchange during rest, activity, and changing environmental conditions.
This article is for general education and is not medical advice. Talk to a qualified health professional about any medical concern.
Sources: Guyton and Hall Textbook of Medical Physiology; West’s Respiratory Physiology: The Essentials; Boron and Boulpaep Medical Physiology.