Intervertebral discs absorb shock by compressing under pressure and distributing forces between the bones of the spine. Their flexible, water-rich structure cushions everyday movements while allowing the vertebrae to bend, twist, and support body weight.
These discs are an important part of human anatomy because they combine mechanical support with flexibility. Every time you walk, sit, lift an object, or change position, the discs help manage forces that would otherwise act more directly on the vertebrae and their joints.
What Are Intervertebral Discs?
Intervertebral discs are cartilage-based cushions located between the vertebrae of the spine. There are typically 23 discs in the human spine, extending from the neck (cervical region) to the lower back (lumbar region).
Each disc forms a joint between adjacent vertebral bodies. Together, the discs contribute to spinal height, maintain space between vertebrae, and permit small movements that add up to substantial flexibility across the spine.
The Two Main Parts of a Disc
- Annulus fibrosus: A strong outer ring of layered fibrocartilage containing collagen fibers that resist stretching, twisting, and excessive deformation.
- Nucleus pulposus: A soft, water-rich central region containing molecules that attract water and help the disc resist compression.
Thin cartilage endplates separate each disc from the vertebral bodies above and below it. These endplates help transfer forces and allow nutrients to reach disc tissue, which has a limited direct blood supply in adulthood.
Discs do not control posture independently. Muscles, ligaments, and spinal joints work together to stabilize the vertebrae, as explained in Posture Control and Core Stability.
How Intervertebral Discs Absorb Shock
When the spine experiences a compressive force, the nucleus pulposus develops internal pressure and transfers forces outward toward the annulus fibrosus. The annulus resists this outward expansion, allowing the disc to deform in a controlled way rather than collapsing freely.
What Happens During Compression?
- Force reaches the disc: Standing, walking, or lifting places a compressive load on the vertebral bodies.
- Internal pressure increases: The water-rich nucleus resists compression and transfers pressure in several directions.
- The outer ring provides resistance: Collagen fibers in the annulus limit outward expansion and help distribute the load.
- The disc recovers: When loading decreases, elastic recoil and gradual fluid movement help restore disc height and shape.
This behavior is called viscoelasticity: disc tissue responds both elastically and over time. Recovery is not always immediate, especially after prolonged compression.
An Everyday Example: Carrying Groceries
Imagine lifting a 10-kilogram grocery bag from the floor. The bag weighs approximately 98 newtons under Earth’s gravity, but the compressive force experienced by the lower spinal discs can be considerably greater because of the body’s position and the forces generated by back muscles.
Holding the bag close to your body reduces the distance between the load and your spine, generally decreasing the muscular effort needed to resist forward bending. The discs still carry compression, but the mechanical demands differ from lifting the same bag with outstretched arms.
Load Distribution and Pressure Management
Intervertebral discs spread compressive forces across the vertebral endplates. This helps prevent loads from concentrating at a single small contact point, although spinal joints, ligaments, and muscles also share mechanical demands.
Spinal shape affects how these forces travel through the body. The natural curves described in Spinal Curvatures and Load Distribution help explain why spinal alignment influences loading.
For a broader explanation of how vertebrae and surrounding tissues support body weight, see Load Bearing in the Spine.
How Different Activities Change Disc Loading
| Activity | Typical Mechanical Effect |
|---|---|
| Standing upright | Body weight produces sustained compression through the spinal column. |
| Sitting | Disc loading varies with posture, back support, and muscle activity. |
| Forward bending | Changes pressure distribution and increases demands on certain disc structures. |
| Lifting a heavy object | Combines external weight with forces produced by supporting muscles. |
| Lying down | Generally reduces axial compression and permits gradual disc rehydration. |
No single posture produces the same disc pressure in every person. Load magnitude, movement speed, spinal position, and individual anatomy all influence the mechanical response.
Disc Hydration and Changes Throughout the Day
Water is central to disc mechanics. The nucleus pulposus contains a high concentration of proteoglycans, molecules that attract water and help the tissue resist compression. Water content varies with age and disc condition, and the nucleus of a young, healthy disc can contain roughly 80% water or more.
During prolonged upright activity, compression gradually drives some fluid out of the discs. When loading decreases during rest, water can move back into the tissue. This daily fluid exchange contributes to small changes in overall height, with people generally measuring slightly taller after sleeping than at the end of the day.
Drinking adequate water supports normal body function, but drinking extra water does not directly reverse disc degeneration. Disc hydration depends on tissue composition, mechanical loading, and the ability of water and nutrients to move through surrounding structures.
Discs are one component of The Axial Skeleton, which provides the framework for supporting the head and trunk while protecting the spinal cord.
How Intervertebral Discs Change With Age
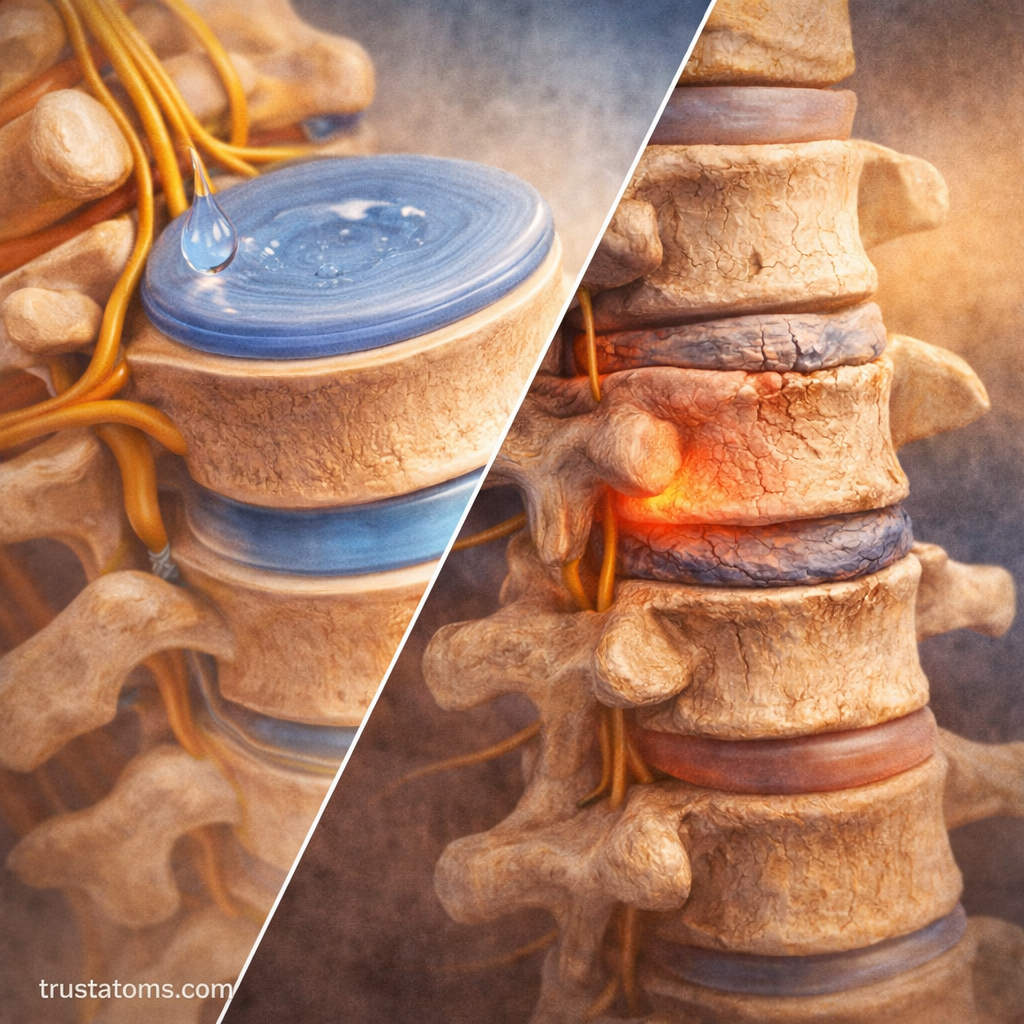
Disc composition changes throughout adulthood. The nucleus pulposus may lose proteoglycans and water, while the annulus can develop structural changes that alter how forces are distributed.
Some discs gradually lose height, become less flexible, or develop fissures. These changes can affect the mechanics of neighboring vertebrae and facet joints. However, degeneration is not automatically a disease, and many people have age-related disc changes without experiencing pain.
Common Disc Conditions and Their Symptoms
Disc-related problems can develop through a combination of aging, genetics, repetitive loading, and injury. Common conditions include:
- Disc bulge: A broad extension of disc tissue beyond its usual boundary.
- Disc herniation: A localized displacement of disc material beyond the normal disc space, sometimes irritating or compressing a nearby nerve.
- Degenerative disc disease: A clinical term used when degenerative disc changes are associated with symptoms, rather than simply describing normal aging.
Possible symptoms include localized back or neck pain, radiating pain, tingling, numbness, or muscle weakness. Yet imaging findings alone cannot establish whether a particular disc is responsible for symptoms.
New loss of bladder or bowel control, numbness around the groin, or severe or progressive leg weakness requires urgent medical evaluation because these symptoms may indicate serious nerve compression.
Practical Ways to Support Disc Health
Discs cannot be protected from every age-related change, but everyday habits can help maintain spinal function and reduce unnecessary strain.
- Stay physically active: Regular walking, swimming, and appropriately paced resistance exercise support spinal muscles and general mobility.
- Change positions regularly: Alternate sitting, standing, and movement rather than remaining in one position for long periods.
- Use manageable lifting techniques: Keep loads close, avoid unnecessary twisting under heavy loads, and use your hips and legs to assist.
- Strengthen supporting muscles: Progressive exercises for the trunk, hips, and back can improve physical capacity.
- Avoid smoking: Smoking is associated with disc degeneration and can adversely affect tissue health.
There is no universally perfect sitting posture or lifting position. Comfortable movement, sufficient strength, and appropriate exposure to physical loads are generally more useful goals than trying to keep the spine completely motionless.
Frequently Asked Questions
Do intervertebral discs absorb all the shock in the spine?
No. Discs cushion and distribute compressive forces, but muscles, ligaments, facet joints, and the natural spinal curves also influence how impacts are managed. Shock absorption is a combined function of several structures.
Can a damaged intervertebral disc heal?
Discs have limited healing capacity because much of their tissue has little direct blood supply. Some herniations shrink over time, and symptoms can improve with conservative treatment, but complete restoration of the original disc structure is not guaranteed.
Why are intervertebral discs thicker in the lower back?
Lumbar discs are generally larger and thicker than cervical discs because the lower spine must accommodate substantial body weight and mechanical loading. Their size and structure also allow movement while helping stabilize the lumbar vertebrae.
Intervertebral discs function as adaptable cushions, using internal fluid pressure and strong collagen layers to manage forces between vertebrae. Their condition changes with age, but structural changes do not always cause symptoms. Understanding how discs respond to loading helps explain why regular movement, physical conditioning, and sensible lifting habits support spinal function.
This article is for general education and is not medical advice. Talk to a qualified health professional about any medical concern.
Sources: Gray’s Anatomy: The Anatomical Basis of Clinical Practice; NCBI Bookshelf, StatPearls: Anatomy, Back, Intervertebral Discs; American Academy of Orthopaedic Surgeons, OrthoInfo.