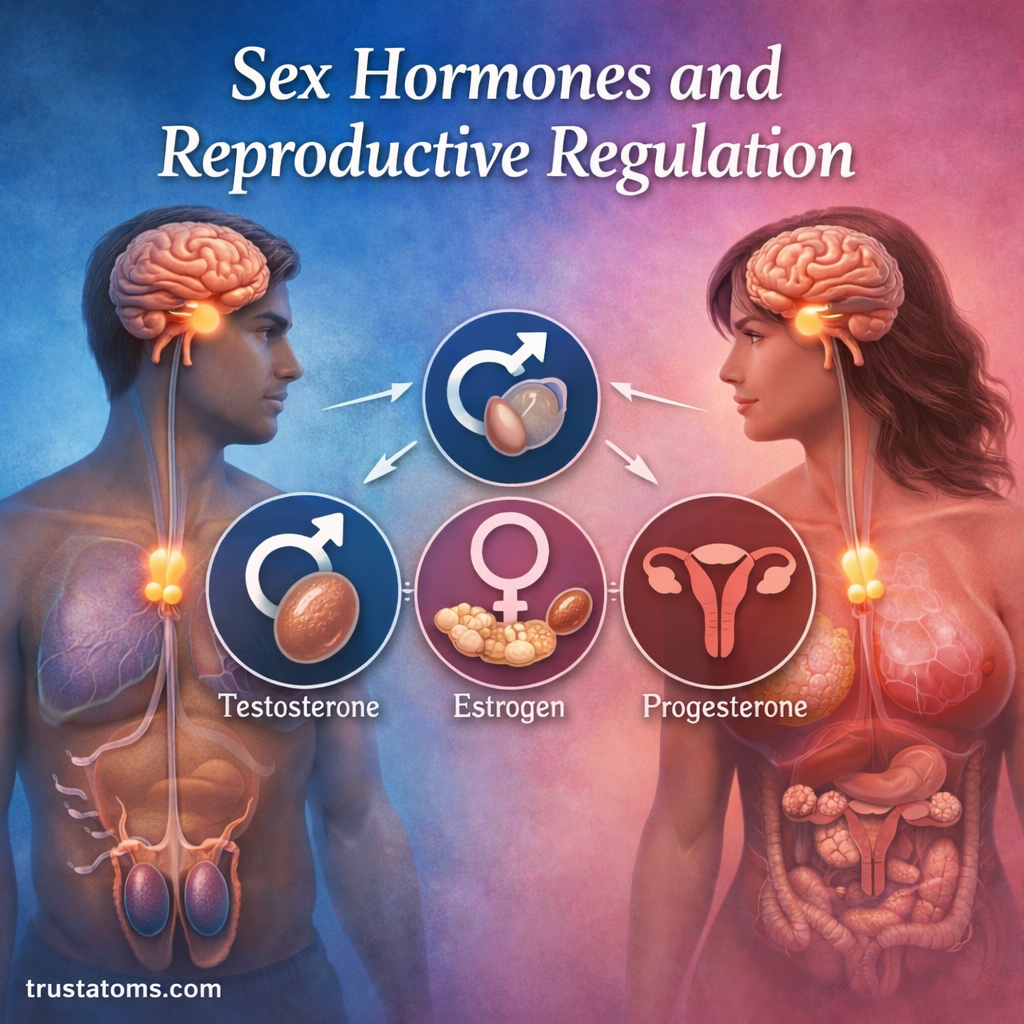
Sex hormones are chemical messengers that regulate reproductive development, fertility, and the function of reproductive organs. Testosterone, estrogen, and progesterone work with hormones from the brain and pituitary gland to control sperm production, menstrual cycles, ovulation, and reproductive maturation.
These hormones connect the endocrine and reproductive systems, making them an important part of human anatomy. Their changing concentrations regulate everything from puberty and fertility to secondary sexual characteristics and reproductive cycles.
What Are Sex Hormones?
Sex hormones are steroid hormones made primarily from cholesterol. The testes and ovaries produce substantial amounts, while the adrenal glands and other tissues contribute to hormone production and conversion.
The three major groups are androgens, estrogens, and progestogens. Testosterone is an androgen, estradiol is an estrogen, and progesterone is the principal naturally occurring progestogen.
All three are present in people of both sexes, although their typical concentrations and reproductive functions differ. They act by binding to receptors in target cells, influencing gene activity and cellular functions.
Major Sex Hormones and Their Functions
Testosterone and Androgens
Testosterone is the primary male sex hormone, though it is present in both sexes.
In males, testosterone is produced mainly by Leydig cells in the testes. It supports reproductive organ development, sperm production, muscle growth, bone maintenance, and the development of characteristics such as facial hair and a deeper voice.
Some testosterone is converted into dihydrotestosterone, a more potent androgen in certain tissues. In females, smaller amounts of testosterone and related androgens contribute to normal physiological functions, including sexual desire.
Estrogen and Reproductive Development
Estrogen is the primary female sex hormone group, with several forms such as estradiol, the predominant estrogen during the reproductive years.
Estrogens support breast development, reproductive tissue maintenance, bone health, and growth of the uterine lining. Estradiol also helps regulate follicle development and the hormonal events leading to ovulation.
Estrogen is present in males as well, where it contributes to bone health and reproductive physiology. Its effects depend on the tissue, receptor type, and circulating hormone concentration.
Progesterone and Pregnancy Preparation
Progesterone is produced mainly by the corpus luteum after ovulation and, during pregnancy, increasingly by the placenta. It changes the uterine lining into a state that can support implantation and early pregnancy.
Progesterone also reduces uterine contractility and helps regulate the menstrual cycle. If pregnancy does not occur, the corpus luteum breaks down and progesterone levels fall, contributing to menstruation.
How the Hypothalamic-Pituitary-Gonadal Axis Works
The hypothalamic-pituitary-gonadal axis, or HPG axis, is the main hormonal control system for reproductive function. It connects three structures through signals carried in the bloodstream.
- Hypothalamus: Releases gonadotropin-releasing hormone (GnRH) in pulses.
- Anterior pituitary: Responds to GnRH by releasing luteinizing hormone (LH) and follicle-stimulating hormone (FSH).
- Gonads: The testes or ovaries respond to LH and FSH by supporting gamete development and producing sex hormones.
- Feedback: Sex hormones and inhibin influence the hypothalamus and pituitary, adjusting subsequent hormone release.
GnRH pulsatility matters because continuous stimulation does not produce the same response as normal pulses. The timing and strength of hormonal signals help determine how reproductive tissues respond.
Hormonal Regulation in Males
In males, the HPG axis generally maintains ongoing testosterone production and sperm development rather than a monthly reproductive cycle.
LH stimulates Leydig cells to produce testosterone. FSH acts on Sertoli cells, which support developing sperm cells inside the seminiferous tubules. High local testosterone concentrations are also necessary for normal sperm production.
Testosterone and its metabolites provide negative feedback to the hypothalamus and pituitary. Sertoli cells release inhibin B, which helps regulate FSH secretion.
Although testosterone secretion varies throughout the day, its regulation does not follow the same cyclical pattern as ovarian hormone production. Reproductive hormone levels also change with age and health conditions.
Hormonal Regulation in Females
In females of reproductive age, ovarian hormones typically fluctuate through the menstrual cycle. These changes coordinate follicle development, ovulation, and preparation of the uterine lining.
The sequence is explained in greater detail in Menstrual Cycle Phases and Hormonal Control.
| Cycle Stage | Main Hormonal Events | Reproductive Changes |
|---|---|---|
| Follicular phase | FSH supports follicle growth; estradiol rises. | Ovarian follicles develop and the uterine lining grows. |
| Ovulation | Sustained high estradiol triggers an LH surge. | A mature follicle releases an oocyte. |
| Luteal phase | The corpus luteum produces progesterone and estrogen. | The uterine lining becomes more suitable for implantation. |
| Menstruation | Progesterone and estrogen decline if pregnancy is not established. | The uterine lining is shed. |
Cycle length varies naturally. The familiar 28-day cycle is a teaching example rather than a fixed schedule, and ovulation does not always occur on day 14.
Negative and Positive Hormonal Feedback
Feedback mechanisms allow reproductive hormones to regulate their own production indirectly through the hypothalamus and pituitary. Most reproductive hormone regulation uses negative feedback.
Negative Feedback Maintains Regulation
When circulating sex hormone concentrations rise, they often reduce GnRH, LH, or FSH secretion. This helps prevent uncontrolled stimulation of the gonads.
For example, testosterone suppresses parts of the HPG axis in males. Inhibin provides additional regulation of FSH in both sexes.
Positive Feedback Triggers Ovulation
Near ovulation, sustained high estradiol concentrations temporarily produce positive feedback. This increases pituitary responsiveness and contributes to the LH surge that triggers ovulation.
After ovulation, progesterone and estrogen from the corpus luteum restore predominantly negative feedback. Reproductive Hormones and Regulation provides a broader explanation of these endocrine control mechanisms.
Sex Hormones During Puberty and Pregnancy

Puberty begins when the HPG axis increases its activity, stimulating greater gonadal hormone production. Rising testosterone supports testicular growth, sperm production, and male secondary sexual characteristics.
In females, increasing ovarian estrogen supports breast development and reproductive maturation. Menstrual cycles begin as the reproductive system develops, although early cycles may not consistently include ovulation.
During pregnancy, the hormonal environment changes substantially. After implantation, developing placental tissue produces human chorionic gonadotropin (hCG), which maintains the corpus luteum during early pregnancy.
The placenta later becomes a major source of progesterone and estrogen. These hormones help maintain the uterine environment, support maternal physiological adaptations, and prepare reproductive tissues for childbirth.
Sex hormones can also influence sexual motivation and aspects of behavior, but bonding and relationships involve many neural, psychological, and social factors rather than a single hormone.
Factors That Influence Sex Hormone Levels
Hormone concentrations change with age, reproductive stage, time of day, and overall health. Several conditions can also disrupt normal HPG axis signaling.
- Age: Ovarian estrogen and progesterone production change during the menopausal transition, while testosterone levels may decline gradually in some aging males.
- Nutrition and energy availability: Severe energy deficiency can suppress reproductive hormone signaling.
- Stress and illness: Significant physiological stress may alter GnRH secretion and reproductive function.
- Medical conditions: Polycystic ovary syndrome, hypogonadism, and pituitary disorders can affect hormone levels and fertility.
- Medications: Hormonal contraceptives, certain treatments, and externally administered hormones can change endocrine feedback.
Hormone measurements must be interpreted in context. A result considered typical at one reproductive stage or time of day may not be appropriate for another.
Frequently Asked Questions
What are the three main sex hormones?
Testosterone, estrogen, and progesterone are the main sex hormones commonly discussed in human reproductive physiology. All are present in both sexes, although their concentrations and functions differ.
How does the brain control reproductive hormones?
The hypothalamus releases GnRH, which stimulates the anterior pituitary to produce LH and FSH. These hormones act on the testes or ovaries, while sex hormones and inhibin provide feedback that adjusts further secretion.
Why do estrogen and progesterone change during the menstrual cycle?
Estradiol rises as ovarian follicles develop, helping prepare the uterine lining and contributing to the LH surge. Progesterone rises after ovulation because the corpus luteum produces it, then falls if pregnancy is not established.
Sex hormones regulate reproduction through coordinated signals between the hypothalamus, pituitary gland, and gonads. Their feedback mechanisms allow hormone production to change during puberty, menstrual cycles, sperm development, and pregnancy while also influencing tissues such as bone and muscle.
This article is for general education and is not medical advice. Talk to a qualified health professional about any medical concern.
Sources: Guyton and Hall Textbook of Medical Physiology; Williams Textbook of Endocrinology; Endotext, National Center for Biotechnology Information.