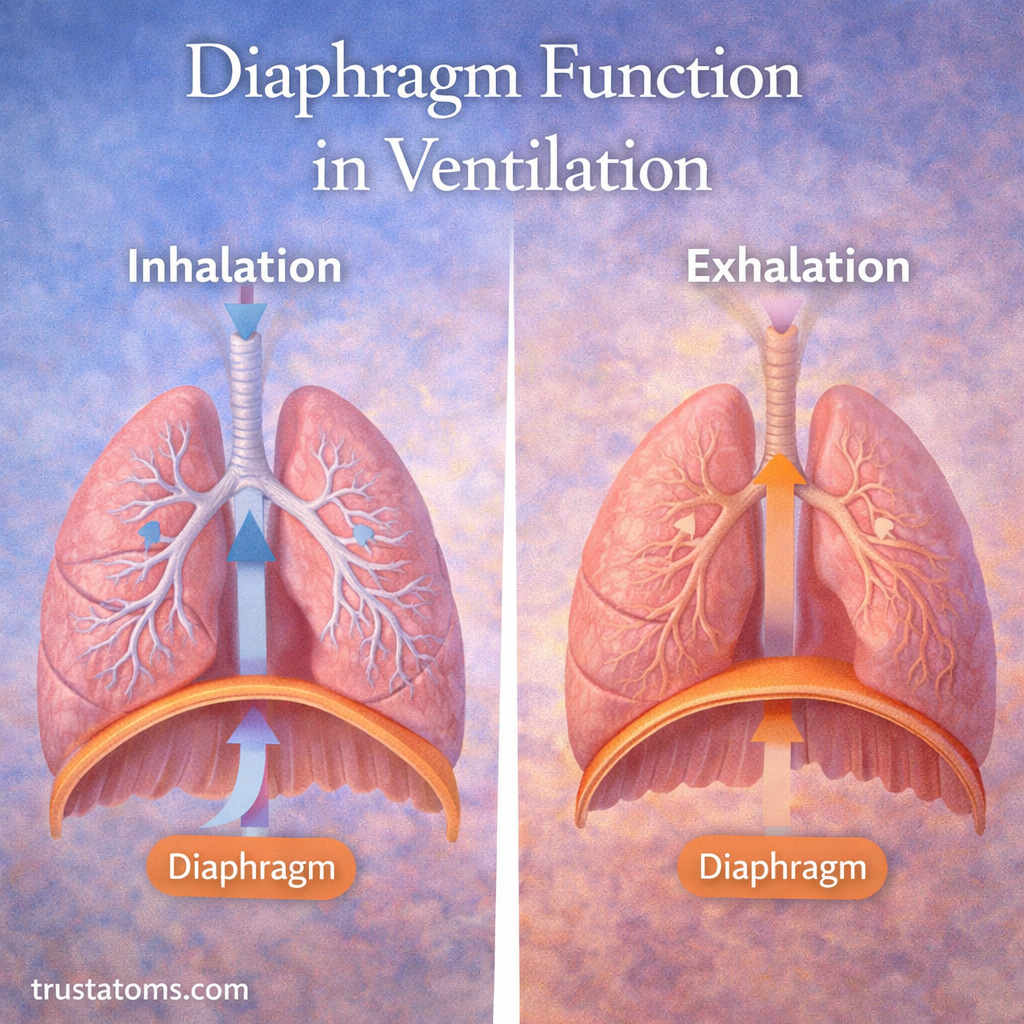
The diaphragm is the primary muscle responsible for breathing. It controls ventilation by contracting and flattening to draw air into the lungs, then relaxing to help air flow out during normal exhalation.
This dome-shaped muscle separates the chest from the abdomen and changes the volume and pressure inside the thoracic cavity with each breath. Understanding its structure and movement connects human anatomy with the physical mechanisms that allow oxygen to enter the body and carbon dioxide to leave.
What Is the Diaphragm?
The diaphragm is a broad, dome-shaped sheet of skeletal muscle and connective tissue located beneath the lungs. It forms the floor of the thoracic cavity and separates the organs of the chest from those of the abdomen.
Its muscular fibers attach to the lower ribs, sternum, and lumbar vertebrae, converging toward a central tendon. When relaxed, the diaphragm curves upward into the chest. During contraction, its domes descend, expanding the space available for the lungs.
Although the diaphragm performs most of the work during quiet inhalation, it operates alongside muscles that move the rib cage. Their functions are explained in Respiratory Muscles Beyond the Diaphragm.
What Is Ventilation?
Pulmonary ventilation is the mechanical movement of air into and out of the lungs. It consists of inhalation, when air enters, and exhalation, when air leaves. Ventilation differs from gas exchange, which occurs when oxygen and carbon dioxide move between alveolar air and pulmonary capillary blood.
Breathing frequency and depth change according to the body’s needs. The relationship between these variables is explored in Respiratory Rate and Ventilation Control.
One major purpose of ventilation is to maintain appropriate carbon dioxide levels. How breathing removes this metabolic waste product is explained in Carbon Dioxide Removal and Ventilation.
How the Diaphragm Works During Inhalation
Inhalation is normally an active process requiring muscle contraction. When the diaphragm contracts, its central tendon moves downward, increasing the vertical dimension of the chest cavity.
- The phrenic nerves deliver motor signals that activate the diaphragm.
- The diaphragm contracts and its domes descend toward the abdomen.
- Thoracic cavity volume increases, and pressure within the pleural space becomes more negative.
- The lungs expand, lowering alveolar pressure slightly below atmospheric pressure.
- Air flows into the lungs until the pressure difference decreases.
The lungs do not actively pull in air using their own muscles. Instead, they expand because the surrounding chest wall and diaphragm change the pressure acting on them.
How the Diaphragm Works During Exhalation
During quiet breathing, exhalation is usually passive. The diaphragm relaxes while the elastic recoil of the lungs and chest wall helps reduce lung volume.
- Diaphragm activation decreases, allowing the muscle to relax.
- The diaphragm rises toward its resting dome shape.
- The lungs recoil, reducing their volume.
- Alveolar pressure rises slightly above atmospheric pressure.
- Air moves outward until the pressure difference disappears.
During forceful exhalation, such as coughing or vigorous exercise, additional muscles actively compress the abdomen and chest to expel air more rapidly.
How Diaphragm Movement Changes Lung Pressure
Air moves because of pressure differences between the atmosphere and the alveoli. Changes in thoracic volume alter the pressure inside the lungs, allowing air to enter or leave.
At rest between breaths, alveolar pressure is approximately equal to atmospheric pressure. During inhalation, it becomes slightly lower; during exhalation, it becomes slightly higher.
| Feature | Inhalation | Quiet Exhalation |
|---|---|---|
| Diaphragm | Contracts and descends | Relaxes and rises |
| Thoracic volume | Increases | Decreases |
| Alveolar pressure | Falls below atmospheric pressure | Rises above atmospheric pressure |
| Airflow | Into the lungs | Out of the lungs |
| Muscle effort | Active | Mostly passive |
This relationship is consistent with Boyle’s law: for a fixed amount of gas at constant temperature, pressure and volume vary inversely. Real lungs are more complex because airflow continuously changes the amount of gas present.
A Practical Example: Breathing at Rest
Consider a healthy adult sitting quietly and breathing 12 times per minute. If each breath moves approximately 500 milliliters of air, the total minute ventilation is 500 × 12 = 6,000 milliliters, or 6 liters per minute.
Each inhalation begins with diaphragm contraction, while each quiet exhalation occurs mainly through relaxation and elastic recoil. The amount of air moved varies with body size, activity, and respiratory health.
Not all 6 liters participate directly in gas exchange because some air remains in the conducting airways. Nevertheless, the diaphragm supplies the mechanical movement needed to maintain this continuous airflow.
Role of the Diaphragm in Deep and Forced Breathing
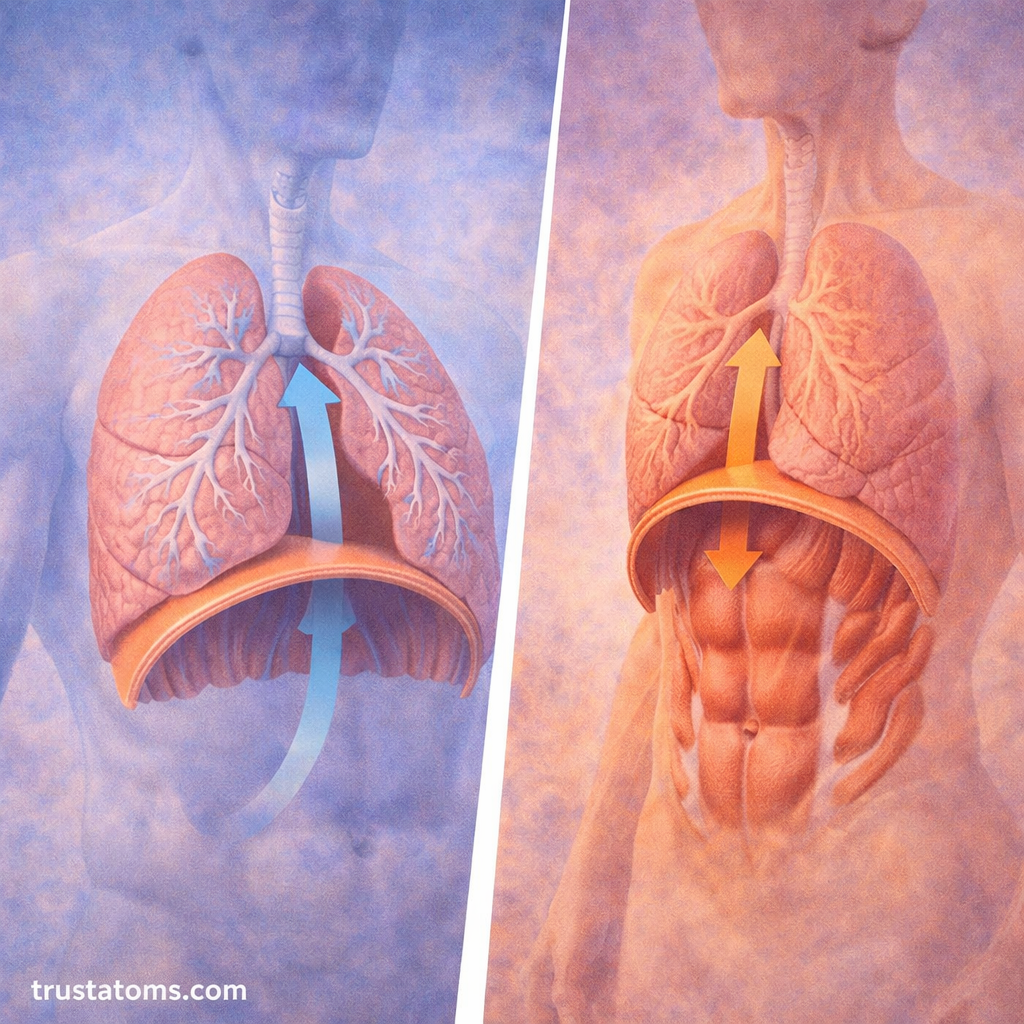
During deep inhalation, the diaphragm contracts more strongly and descends farther than during quiet breathing. External intercostal muscles and, when needed, accessory inspiratory muscles help expand the rib cage.
Forced exhalation works differently. Abdominal muscles contract, increasing abdominal pressure and pushing the relaxed diaphragm upward. Internal intercostal muscles can also help move the ribs downward, reducing thoracic volume.
The nervous system adjusts these movements according to physical activity and changing blood gas levels. The brainstem mechanisms behind these adjustments are discussed in Neural Control of Breathing.
How the Phrenic Nerve Controls the Diaphragm
The diaphragm receives its main motor supply from the left and right phrenic nerves, which originate from spinal cord segments C3, C4, and C5. These nerves transmit signals from respiratory motor pathways to the diaphragm muscle fibers.
Respiratory centers in the brainstem generate and adjust the basic breathing rhythm. Sensory information about carbon dioxide, blood pH, and oxygen helps influence ventilation.
Breathing can also be modified voluntarily during speaking, singing, or breath-holding. However, automatic respiratory control continues to operate and normally restores breathing when the body needs to regulate blood gases.
What Happens When the Diaphragm Is Weak or Damaged?
Diaphragm dysfunction can make breathing more difficult, particularly during physical activity or when lying flat. The effects depend on whether one or both sides are affected and whether other respiratory muscles can compensate.
- Phrenic nerve injury: Damage to the nerve can weaken or paralyze the diaphragm on the affected side.
- Neuromuscular disorders: Conditions affecting nerves or skeletal muscles may reduce diaphragm strength.
- Diaphragmatic hernia: An opening or defect in the diaphragm may allow abdominal organs to move into the chest.
- Respiratory muscle fatigue: Prolonged excessive breathing effort can contribute to respiratory muscle weakness or fatigue.
Clinicians may assess diaphragm movement using ultrasound or other imaging techniques, along with respiratory muscle strength and lung function measurements. Severe bilateral dysfunction can require assisted ventilation.
Supporting Healthy Diaphragm Function
Regular physical activity supports overall respiratory muscle conditioning. Maintaining good posture and avoiding smoking can also benefit respiratory health.
Diaphragmatic breathing exercises encourage controlled abdominal movement during inhalation and may help selected patients improve breathing patterns or reduce unnecessary accessory muscle use. However, they do not automatically increase lung capacity or correct every cause of breathlessness.
People with persistent shortness of breath, known respiratory disease, or suspected diaphragm weakness should seek professional evaluation rather than relying on breathing exercises alone.
Frequently Asked Questions
Does the diaphragm contract during inhalation or exhalation?
The diaphragm contracts during inhalation, flattening and descending to increase thoracic volume. During normal quiet exhalation, it relaxes and returns toward its dome shape as the lungs recoil.
Can you breathe without a functioning diaphragm?
Some breathing may remain possible with weakness or paralysis on one side because the opposite diaphragm and other respiratory muscles can compensate. Severe dysfunction affecting both sides can make adequate independent ventilation impossible and may require mechanical assistance.
Why does the abdomen move outward during diaphragmatic breathing?
As the diaphragm contracts and descends, it displaces abdominal contents and increases pressure within the abdominal cavity. If the abdominal wall remains relaxed, this displacement causes the abdomen to move outward during inhalation.
The diaphragm generates the pressure changes that make normal inhalation possible, while its relaxation helps permit passive exhalation. Its coordination with the phrenic nerves, rib cage muscles, and respiratory control centers allows breathing to adapt from quiet rest to strenuous activity. Understanding these mechanisms also explains why diaphragm weakness can interfere with ventilation even when the lungs themselves are structurally intact.
This article is for general education and is not medical advice. Talk to a qualified health professional about any medical concern.
Sources: Hall, Guyton and Hall Textbook of Medical Physiology; West and Luks, West’s Respiratory Physiology: The Essentials; OpenStax, Anatomy and Physiology 2e.